Ventilator Breathing Circuits
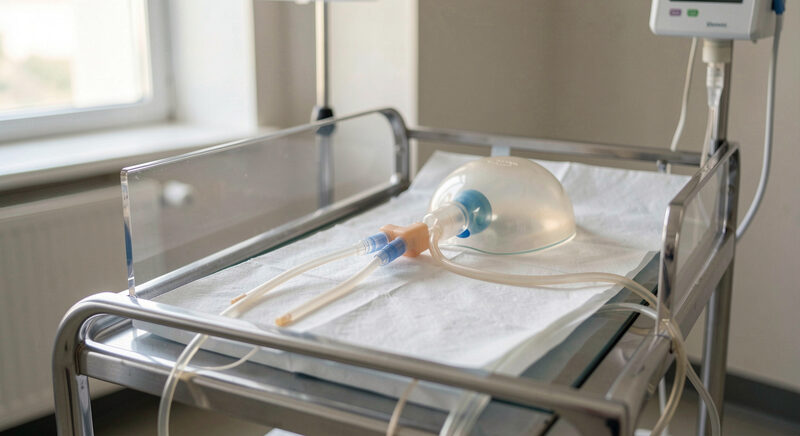
A ventilator breathing circuit carries gas from the machine to the patient and back again. It is the part of the ventilator that touches the patient most directly, and its size, compliance and connectors decide whether the volume set on the screen is the volume that reaches the lungs. This guide covers how adult, paediatric and neonatal circuits are built, why their dimensions differ, and what the relevant standards require of them.
What is inside a ventilator breathing circuit?
A two-limb circuit has an inspiratory limb, an expiratory limb and a Y-piece that joins them at the patient end. Corrugated tubing connects these parts and resists kinking when the patient moves. Depending on the setup, the assembly also carries a water trap, a temperature probe, a filter, a nebulizer port, and a catheter mount or elbow at the airway. The machine end connects to the ventilator's inspiratory and expiratory ports. Some circuits are coaxial, with one tube inside another, which saves space and can reduce heat loss, though it changes the way the limb is inspected for condensate.
How do adult, paediatric and neonatal circuits differ?
The main differences are diameter, length and compliance. An adult circuit is wide enough to keep resistance low at high flows, and long enough for the patient to turn in bed. Paediatric and neonatal circuits use narrower tubing to reduce dead space and compressible volume, the internal volume of the circuit that the ventilator must fill before gas reaches the patient. In a neonate with a tidal volume of a few millilitres, a compliant adult limb would absorb much of each breath. Neonatal circuits are therefore made from stiffer, low compliance tubing and supplied in short lengths, often with smaller water traps and lighter connectors so the assembly does not pull on the airway.
Why does compressible volume matter so much in small patients?
Compressible volume is the gas that is stored in the circuit rather than delivered. It rises with tube length and with how easily the tubing expands under pressure. When the ventilator pushes a breath, part of that volume stays in the tubing, and the fraction lost is larger when the set tidal volume is small. This is why a neonatal circuit is matched to the patient rather than reused from an adult trolley, and why the circuit length is kept to what is needed. A circuit that is too large for the patient can make ventilation look adequate on the machine while the delivered volume is short.
What do the standards require of a breathing set?
Breathing sets and breathing tubes are covered by ISO 5367, which applies to sets used with anaesthetic breathing systems, ventilator breathing systems, humidifiers and nebulizers. It specifies minimum requirements for leakage, flow resistance and the designation of a tube by its nominal overall length, measured in metres in the resting condition. Connectors follow ISO 5356-1, which defines the 22 mm and 15 mm conical fittings that let parts from different makers join. The ISO 5367 standard also provides for coaxial and other multi-lumen sets. Together these rules mean a replacement limb can be judged on measurable properties rather than on appearance.
How does the circuit connect to the patient?
At the patient end, the Y-piece usually meets a catheter mount or a swivel elbow, which absorbs movement before it reaches the tube. The catheter mounts guide explains how that flexible link is built and why a double swivel matters. A filter or heat and moisture exchanger often sits between the Y-piece and the airway, covered in the HME filters guide. Each added component contributes dead space and resistance, so the assembly is kept as short and as light as the clinical need allows.
Where do condensation and water traps fit in?
If the circuit is used with a heated humidifier, warm humidified gas cools as it travels and some of its vapour condenses. The liquid gathers at the lowest point of a limb, where a water trap collects it. The water traps guide covers how traps are emptied and checked, and the heated wire circuits guide explains how a heated wire keeps the tube wall warm to reduce that condensation in the first place. Both are part of reading a ventilator circuit in use, not separate subjects.
How circuits are packaged and stored
Ventilator circuits are supplied as a complete assembly, often with the water traps and connectors already fitted, and packaged to keep the internal surfaces clean until use. The label states whether the circuit is sterile or non-sterile, its size, and the standards it meets. Storage matters more than it seems: heat and sunlight age the plastic and can make the tubing stiff, which changes how it behaves under pressure. Circuits are stored flat or on a hanger, not crushed under heavier stock, and the packaging is left sealed until the circuit is needed. When a pack is opened, the whole assembly is checked before it goes near a patient, and parts are not borrowed from another pack unless the connectors and sizes are known to match.
What to check on a ventilator circuit at the bedside
A circuit is checked before use and during use. Before connection, confirm the packaging is intact, the tubing is undamaged, every connector is seated and the correct size is fitted for the patient. After connection, a leak test and a delivered volume check show whether the assembly is sound. During ventilation, watch the limbs for condensate, keep the trap emptied and closed, and listen for any new gurgle or hiss. When a circuit is changed, the same checks are repeated, because a new assembly is a new set of connections. The habit that prevents most circuit problems is simple: look at the whole assembly, not only the numbers on the screen.